Post 1
InnerEcho in fifteen seconds
The ensō, InnerEcho, then haiva and sona.
Geneva · built for Europe
A research initiative in development · looking for partners and funding
haiva 4 gives mental-health practitioners time and attention back. sona 4 stays with their patients between sessions. Voice, measured carefully and shown only to the clinician, connects the two. The AI brings evidence; the clinician decides.
The time a patient takes before answering, and the pauses inside an answer, are among the things haiva measures, against the same patient’s earlier sessions. A fact for the clinician to interpret, never a diagnosis or a score. Illustration with invented values.
1.2 s99.4%
of a patient’s week happens between sessions
3,131
voice features per session in our first version, R3
1.1M+
nodes in the clinical knowledge graph, ICD-11 to SNOMED CT
0
risk scores, anywhere, in line with NICE NG225
Why this matters
The World Health Organization puts the global median at 13 mental-health workers per 100,000 people. Those in practice spend a large share of their time on documentation instead of care.
A weekly session is one hour out of 168. A hard night, a small breakthrough, the early signs of relapse: by the next session most of it has faded.
Studies have repeatedly linked slower speech, longer pauses and flatter pitch with depression. The field is young. InnerEcho measures carefully, compares each value with the patient’s own history, and labels what is not validated.
1 of 168
One week, hour by hour. The lit square is the weekly session; sona is designed for the rest, with the patient’s consent.
The principle
haiva does not make clinical decisions and does not act on its own. It provides measured evidence that flows through the care relationship. Every output stays under the practitioner’s review and control. The clinician validates; the AI provides evidence.
This is not a tool that thinks for the practitioner. It is a tool that helps them see more clearly.
| Automation with a human check | AE-in-the-Care-Loop | |
|---|---|---|
| Who decides | The system proposes a conclusion; a person approves or overrides it | The clinician decides; the system supplies evidence for the decision |
| What the AI produces | Classifications, scores, recommendations | Measures, drafts, sources and open questions, each labelled |
| When the data is poor | A result is produced anyway | “Not measurable”, with the reason |
| What the patient sees | Varies by product | No analysis, ever: their own record, diary and help |

haiva 4 · health ai voice assistant
A clinical intelligence platform for psychiatrists, psychologists and psychotherapists. It extends what a practitioner can perceive and reduces the time spent on work that does not directly serve patients.
Sessions recorded and transcribed with consent for each purpose. Pitch, rhythm, jitter, shimmer, pauses and the timing between two speakers, each against the patient’s own history.
SOAP or DAP notes, reports and invoices drafted from the session. Every sentence cites the moment it comes from. Nothing is final without a signature.
Cross-references what was said with ICD-11, ICD-10-GM and SNOMED CT, and points out gaps in the assessment. A prompt to ask, never a diagnosis.
With consent, two-to-three-minute check-ins between sessions, led by sona, summarised for the practitioner before the next appointment.
Reflective practice on the practitioner’s own speech timing and vocal load, visible to them alone. No emotion, stress or burnout inference: EU law forbids it at work, and we hold that line.
Crisis items reach the Safety inbox and escalate if unacknowledged. Help now works offline and without sign-in. No risk score.
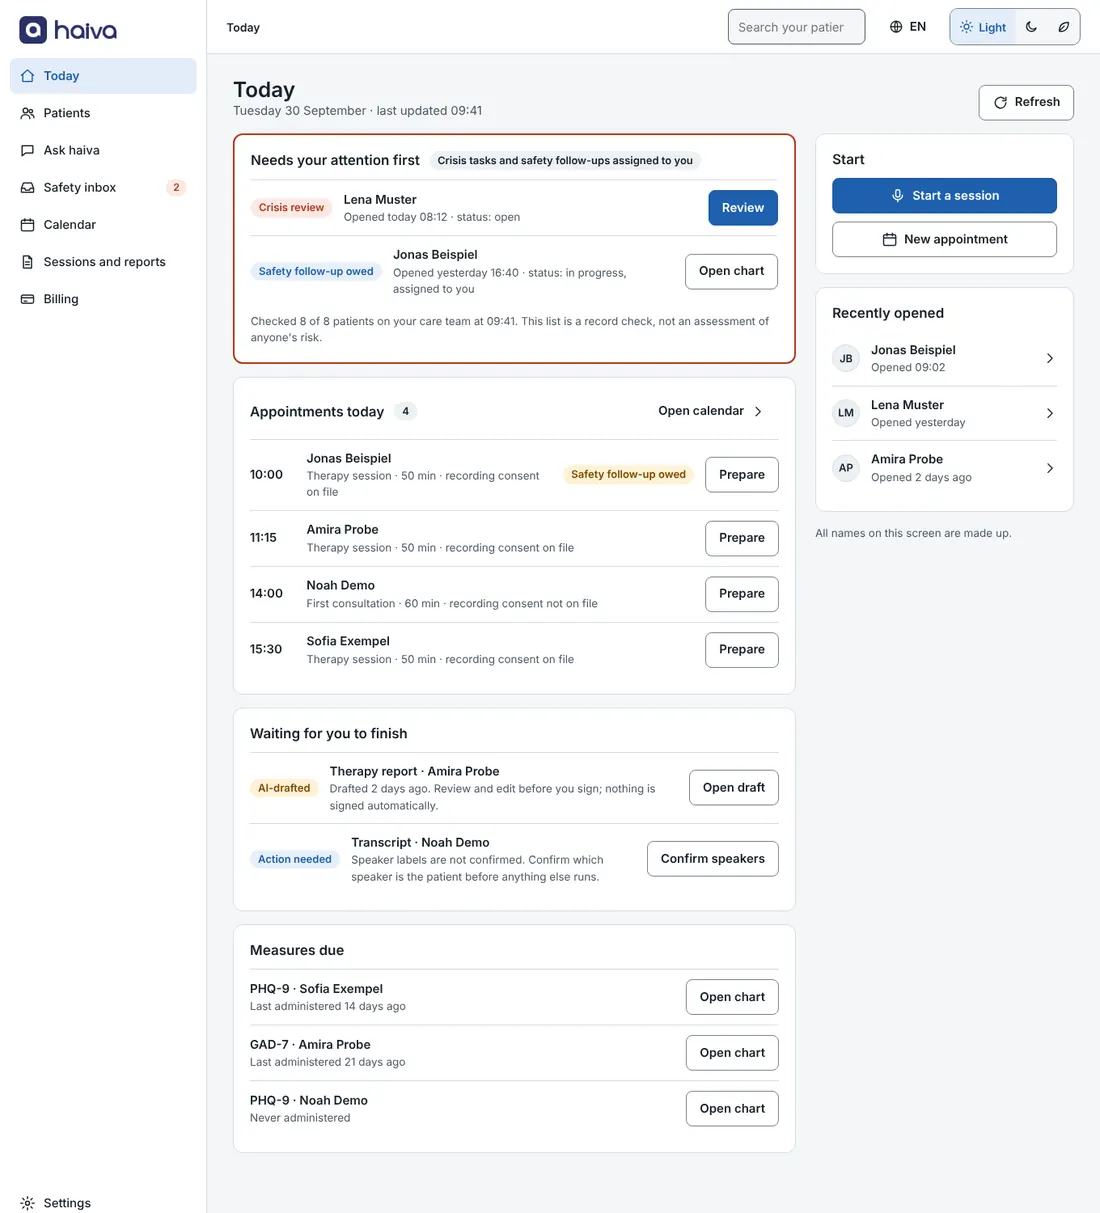
haiva 4 design prototype, made-up data.
Voice at the centre
A recording already exists for the note, so measuring how the patient spoke needs no extra task, only separate consent. Every value is compared with the same patient’s earlier sessions, never with population norms or as a disorder score.
L1a · Timing
Who waits how long before answering, and how that changes over weeks. Does not show mood or speed of thought.
L1b · Acoustics
Measured from the sound with published methods. Does not show sadness, anxiety or flat affect.
L2 · Own range
Each value against this patient’s earlier sessions in the same setup. The clinician decides whether a difference matters.
MED EVO · clinical knowledge
1.1M+
nodes
2.8M+
relationships
Built and running in haiva R3; carried into haiva 4 in its own database, apart from patient data. DSM-5-TR only under licence from its publisher.
Not yet explored in the assessment
Patient presenting with depression.
A prompt to ask. Never a diagnosis.
Example prompt, made-up patient.

sona 4 · for the patient
A companion for adults in active treatment whose practitioner has switched it on. It always says it is an AI, never diagnoses, and points back to people.
Their record stays under their control: a private diary, what sona remembers (readable, correctable, hideable), consent for each use, export at any time. Crisis numbers for the country they are in, offline.
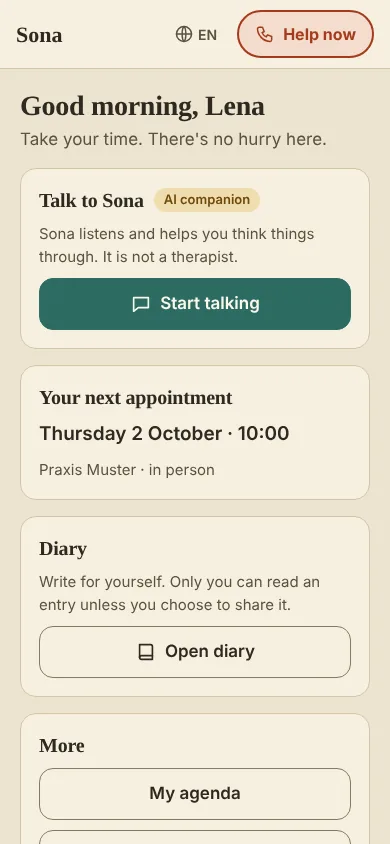
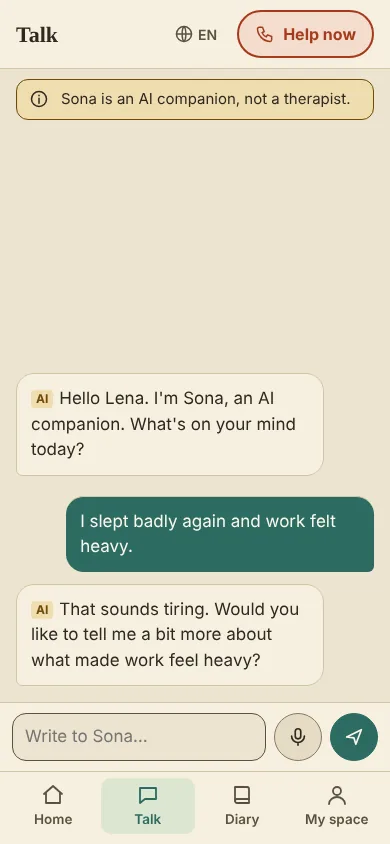
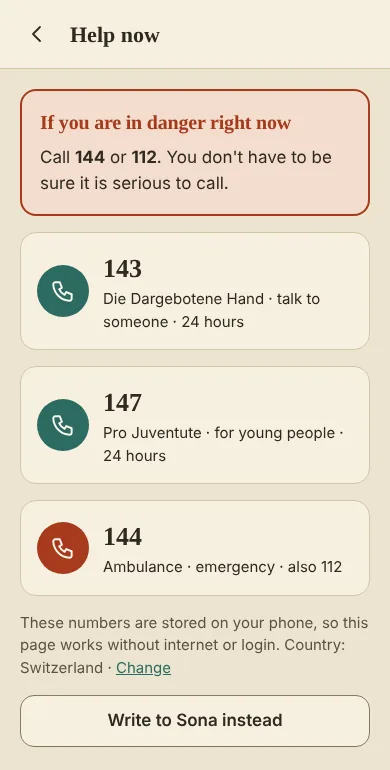
sona 4 design prototype, made-up data.
A complete nutrition pipeline, from a food knowledge graph of more than 627,000 European products to private food notes, brought into sona under its clinical rules. Every claim carries an evidence label.
Safety
A crisis signal reaches a person, not a number.
Open source · MPL-2.0
Open, inspectable and able to run locally. Each works alone; they exchange files and JSON on one session clock, never code. In haiva 4 and sona 4 they sit beside the current pipeline, so the best one can be chosen on evidence.
Capture
Seals audio in short chunks as it records. A stored recording is treated as a hazard, at home, at a checkpoint, in a war. Version 0.10, 213 tests.
Transcripts
Who spoke when, two speakers, benchmarked in the open on recordings with known truth. Ships no models; each listed with its licence.
Measures
Each voice measure with its published source and evidence grade, or “not measurable” with the reason written into the result.
Built for Europe
haiva 4 and sona 4 start in Switzerland because InnerEcho is in Geneva. Everything that depends on a country is a module, customised and adapted. The core never forks.
Crisis resources today
Built on haiva R3 and sona R3
3,131
voice features per session
haiva 4 and sona 4 build on haiva R3 and sona R3, our first working versions. They ran the whole chain end to end on demonstration records and taught us what a clinical product has to do differently. The full story is in the partner room.
Who it serves
psychiatrists, psychologists, psychotherapists
adults in treatment whose practitioner switches sona on
professors, study investigators, students
foundations, philanthropists, impact investors, angels, venture funds
The path
One code base, two editions: what differs is which modules are switched on, enforced on the server and audited. A platform that stays in the lab does not help a single patient.
1 · First
Universities, research programmes, teaching with synthetic patients. Most modules on, all labelled.
2
Study investigators with consenting adults, under ethics approval. A clinical safety lead signs off.
3
Sealed evaluation sets, clinician review, published methods, validation with university partners.
4 · The goal
Practices, clinics, hospitals. A module is on only when its evidence and approvals allow. Certified releases.
Commitments
Nothing becomes part of the record without a practitioner’s signature.
No diagnosis, no score, no reading of their voice.
Crisis signals go to a person to look at.
Help now works without sign-in, network or any switch.
Their own voice is measured only if they switch it on, and only for them.
Research use only with ethics approval and consent for that purpose.
sona ends when therapy ends. Success is measured in care, not minutes.
Every voice value carries its evidence grade and “not validated” label.
On LinkedIn
Short slide documents on what we build, and how, as posted on the InnerEcho Initiative page. Read them here, or download them.
Post 1
The ensō, InnerEcho, then haiva and sona.
Post 6
The patient companion, rebuilt around safety.
Post 7
captavoce™, tramavoce™ and meravoce™, open under MPL-2.0.
Post 8
Clinical knowledge, linked carefully, for research teams.
The slides follow the language of this page. Screens inside them come from our prototypes, in English, and show made-up or demonstration data.
Partner room
For funders, universities, clinicians and future partners. Access by password, on request.
No password yet? Write to us below.
Inside
Partners
The step from research to the clinic is not one a single team takes alone.
InnerEcho offers
InnerEcho is looking for